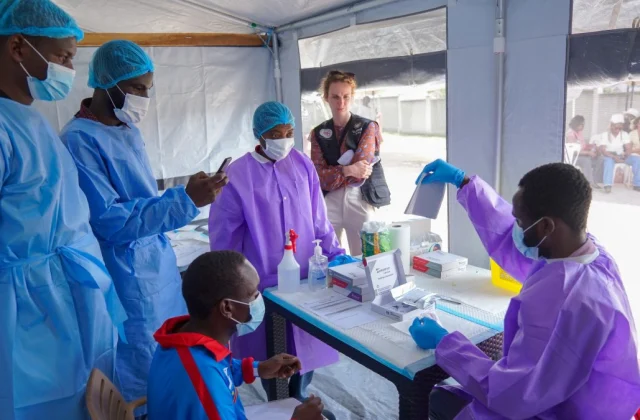
The Democratic Republic of Congo’s Ebola outbreak will remain classified as a public health emergency of international concern, the World Health Organization said Wednesday, as rising infections and deaths collide with armed conflict, funding gaps and limited access to affected communities.
WHO Director-General Tedros Adhanom Ghebreyesus announced the decision after the agency’s Emergency Committee reviewed the outbreak and advised keeping the international emergency designation in place.
“We call for the cooperation of all governments and all partners to scale up the response further, and raise the resources needed to protect communities over the coming months,” Tedros said in a post on X.
He also called on governments and armed groups to protect health workers, treatment centers and emergency crews working in areas where violence has repeatedly interrupted efforts to contain the virus.
The WHO plans to issue updated recommendations for Congo and other countries in the coming days, Tedros said, as the outbreak continues to pose a potential cross-border public health threat.
The epidemic is being driven by the relatively rare Bundibugyo strain of Ebola. It is now Congo’s largest outbreak on record and the second-largest worldwide. WHO figures show more than 11,300 infections and 5,500 deaths since the outbreak was declared May 15.
At the agency’s headquarters in Geneva on Tuesday, Tedros said between 400 and 500 new infections were being recorded each week. The pace highlights how difficult it has been to slow transmission six months after the outbreak began.
The WHO has raised particular concern about the number of people dying before reaching Ebola treatment centers, a sign that patients are not receiving care quickly enough.
About two-thirds of confirmed deaths have taken place outside treatment facilities. Children represent more than one-quarter of confirmed infections and one-third of recorded deaths.
“Children are paying a terrible price,” Tedros said.
An outbreak outpacing previous epidemics
Public health officials have been alarmed by the outbreak’s speed and scale. During its first six months, infections and deaths have climbed at roughly twice the rate seen in the opening half-year of West Africa’s 2014-2016 Ebola epidemic, the largest ever recorded.
That epidemic, which mainly struck Guinea, Liberia and Sierra Leone, eventually infected more than 28,600 people and killed over 11,000, according to the WHO.
Although Congo has endured repeated Ebola outbreaks, none has matched the current epidemic. The country is confronting its 17th outbreak, and the toll has already exceeded the national record established during the 2018-2020 epidemic.
The earlier outbreak, centered in eastern Congo, caused 3,481 infections and 2,299 deaths.
In the current crisis, persistent insecurity, shortages of medical supplies and personnel, and weak coordination among affected regions have all hindered containment.
Health workers, surveillance teams and medical vehicles have come under attack. In some communities, distrust of outsiders has made it harder to identify cases, trace contacts and persuade infected people to seek treatment.
Tedros said insecurity remains among the greatest barriers to ending the outbreak, warning that violence continues to disrupt medical operations.
Medecins Sans Frontieres, also known as Doctors Without Borders, said last week that critical medical supplies and staff were not reaching several outbreak hotspots outside the original epicenter in Ituri province.
A Congolese woman reacts outside the house of a man who died of Ebola as she waits for medical workers to retrieve his body, as aid agencies intensify efforts to contain a new Ebola outbreak involving the Bundibugyo strain, in Quartier Shuni 1, a residential sector in Mongbwalu, Djugu Territory of Ituri province, DRC, May 24, 2026. (Reuters Photo)
The response has also been strained by labor disputes and delays in paying health workers. Some medical personnel have reportedly not received wages since August, leading to strikes and placing additional pressure on an already overstretched health system.
Tedros said the payment delays were slowing operations. The Congolese government has said it is working to address the issue.
Financing is another growing concern. Around $2.9 billion has been pledged for the response, but Africa’s leading public health agency said less than half of that money has actually been disbursed.
The agency has urged international donors to work more closely with the government in Kinshasa so that available funds reach communities in need instead of being diluted by overlapping or duplicated efforts.
Two experimental vaccines to enter clinical trials
As response teams confront those obstacles, the WHO is preparing to deploy two experimental vaccines designed specifically for the Bundibugyo strain, potentially adding a new tool to the fight against the epidemic.
Phase 2 clinical trials are expected to begin Nov. 26 or 27 in Bunia, the capital of northeastern Ituri province and the outbreak’s epicenter.
The WHO announced the plan Tuesday, saying both candidates had completed Phase 1 trials, which focus mainly on safety and the body’s initial immune response.
One candidate, ChAdOx1, is an adenovirus-based vaccine developed by the University of Oxford. The other, mRNA-1469, was created by U.S. pharmaceutical company Moderna using messenger RNA technology, the same broad approach that gained global recognition during the COVID-19 pandemic.
No vaccines or specific treatments for the Bundibugyo strain have yet been approved, increasing the importance of developing products aimed at the virus.
The candidates will be studied through the WHO-supported Tumaini trial, a clinical research framework evaluating multiple vaccines for safety, effectiveness and their ability to generate an immune response.
The study uses ring vaccination, a strategy that prioritizes people who have been in contact with confirmed patients, along with others considered at high risk of infection.
The framework began testing Ervebo, an approved vaccine against the more common Zaire strain of Ebola, on Oct. 23. Researchers are examining whether it may also offer protection against Bundibugyo.
Meg Doherty, the WHO official who leads the agency’s science for health department, said more than 140 people had enrolled in the Tumaini trial and that thousands of additional contacts were expected to take part.
The research is initially based at one site in Bunia, with plans to expand to other locations.
If Phase 2 testing produces acceptable safety and immune-response results, the vaccine candidates could move into larger Phase 3 trials. Those studies would offer more evidence about whether the vaccines can prevent infection or disease.
Ebola is transmitted through direct contact with the bodily fluids of infected people or contaminated materials. The virus can cause severe illness, including hemorrhagic fever, and has killed more than 15,000 people across Africa during the past five decades.